|
Getting your Trinity Audio player ready...
|
The United States has returned to a time, until recently unimaginable, when measles is a persistent threat, not just a sporadic one that can easily be snuffed out.
Even with rigorous effort, it is likely to take years to regain measles elimination status, which the country officially lost Tuesday. In the meantime, Americans will need to embrace strategies, some well worn and some new, to contend with this forgotten menace, more than a dozen experts said in interviews.
Local and state health departments will need more resources to combat outbreaks. Doctors, parents and teachers will need to familiarize themselves with the symptoms and prepare to quarantine anyone who is unvaccinated and exposed for 21 days. Hospitals will need to prepare for an onslaught of patients infected with a highly contagious virus. Public health officials may need new tools to detect, diagnose and stem outbreaks quickly. And they may need to revise the recommended vaccination schedule to protect the most vulnerable.

“We’re really in kind of a new Wild West of our own making,” said Dr. Christopher Monson, an intensive care pediatrician at the University of Rochester.
“Lots of people are going to get sick, and some people are going to die,” he added. “It’s just sad that we’re spending this much energy on things we had already fixed.”
Measles is among the most contagious viruses known. It lingers in the air for hours and infects 9 of every 10 unprotected people who are exposed to it. The illness begins with typical respiratory symptoms, such as a runny nose and cough, then rapidly progresses to characteristic white spots inside the mouth and a rash that spreads down from the hairline to the feet. In some people, the virus may also ravage the lungs, the brain and other organs.
About 11% of measles patients in the United States this year were hospitalized, and 10 people have died.
The Centers for Disease Control and Prevention did not provide responses to questions about its plans to prepare for and address measles outbreaks.
In recent months, the CDC gave states a surprise infusion of $100 million to bolster immunization efforts and improve surveillance of the disease. But that may not be enough.
The costs for immunization drives, case investigation, contact tracing and quarantine can quickly add up. It took $8.7 million to stamp out an outbreak that started at a migrant shelter in Chicago in 2024 and $5.4 million to control a 2025 cluster in New Mexico.
Vaccination Is Essential
Measles cases dropped precipitously after the arrival of the vaccine in 1963. The introduction of a second dose, in 1989, helped the country eliminate the threat. Declining vaccination rates are the main reason the measles virus has reclaimed a foothold in the United States.
Regaining elimination status will require bringing them back up to 95%, a threshold known as herd immunity, to keep the virus from spreading in communities, medical experts said.
Five of the 10 deaths were in children too young to be vaccinated. The remaining were in unvaccinated adults, who might have previously been shielded by herd immunity. “Completely unvaccinated adults getting measles — I mean, that’s going to take us back 30, 40 years,” said Dr. David Hamer, an infectious diseases physician at Boston University.
The number of cases this year has topped 5,400, more than double last year’s tally and the highest since 1991, nearly a decade before the country attained elimination status. About 96% of the known cases this year have been in those who were unvaccinated or whose vaccination status was unknown.
“I have no confidence to think 2027 will be even better,” said Dr. Scott Roberts, an infectious disease doctor at Yale New Haven Health. “I mean, at this rate, it’s looking to be exponentially worse.”
Infection with measles erases the body’s immune memory, leaving patients newly vulnerable even to diseases they already had. It can also cause long-term complications in some people, including subacute sclerosing panencephalitis, a fatal neurological condition that can develop years after the initial illness.
“It’s really a bad disease and dangerous, and I think people need to appreciate that,” Hamer said.
The first dose of the combined measles-mumps-rubella vaccine is typically given at 12 months. But that schedule is devised for a country with low risk of exposure to measles.
“At what point would we modify the vaccine schedule to address this increasing risk?” said Dr. Nathan Lo, an infectious diseases physician and epidemiologist at Stanford University.
Some experts now recommend vaccinating young babies before travel to outbreak areas within the United States. As measles becomes more common, the guidance may need to expand to include all infants, Lo said.
That approach is also complicated, however. Giving the first dose at 6 months is thought to blunt the vaccine’s effectiveness long term. In many parts of the world where measles is endemic — a constant and predictable presence — the first dose is instead routinely given at 9 months, Lo said. Officials may also need to consider a second dose for adults who received only a single shot when they were children.
Decades of studies have shown that the measles vaccine is safe. But messaging urging vaccination has sometimes been too forceful and too dismissive of parents’ concerns about safety, said Mary Politi, a co-director of the Center for Collaborative Care Decisions at Washington University in St. Louis.
People “need more accessible information with stories and relatable experiences so that they don’t feel like they’ll be cast aside if they ask a question,” she added.
The Importance of Early Detection
To stamp out outbreaks, public health officials will need to detect them early, before the virus has had a chance to circulate widely.
At the population level, wastewater surveillance can indicate where measles may be percolating, long before a patient seeks medical care.
Measles “is such an infectious virus that people excrete a lot of it, so just one person in the sewer shed can excrete enough into wastewater that it lights up,” said Alexandria Boehm, a researcher at WastewaterSCAN, an academic initiative that includes 150 wastewater treatment plants.
Wastewater monitoring in Houston picked up genetic material from the measles virus Jan. 7, 2025, two weeks before the first case in the state was confirmed. In Oregon, wastewater testing detected measles 10 weeks before the first case was reported in June 2024. Officials in those communities alerted doctors and public health officials.
The CDC set up the National Wastewater Surveillance System during the COVID-19 pandemic and expanded it to include 1,500 sites, covering nearly half the country’s population. That emergency funding expired at the end of September.
The Trump administration has proposed cutting the program’s budget to about $25 million a year from $125 million.
Educating the US Health System
The elimination of measles in the United States has meant that few American doctors practicing today have had experience with the disease.
“We know what to do about measles — how it spreads, what type of isolation you need, how to clean the environment,” said Dr. Marci Drees, the chief infection prevention officer at ChristianaCare, a health system in Delaware. But, she added, “we just haven’t had to do it in so long that it feels very new for people.”
Some hospitals are conducting drills to train staff members to identify measles symptoms and quickly isolate patients before they put others at risk.
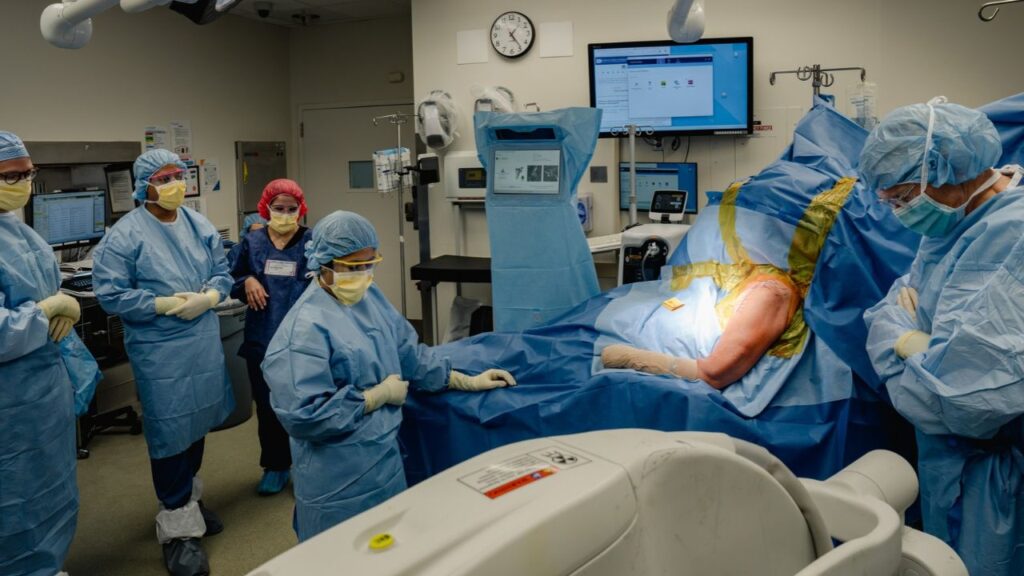
Monson had never seen a measles case until last month, when he treated two school-age siblings who were hospitalized for weeks. To safely transport the patients, the Rochester hospital cleared hallways and blocked off elevators for periods. Even after the children were isolated, staff members worried about the other critically ill patients who might be exposed to the virus by the nurses or respiratory therapists attending to the children.
Having never treated severely sick children with measles, the doctors were also stumped on treatment. Scientific papers on the subject date back to the 1960s and ’70s, so “none of the data is relevant to here and now and where we are,” Monson said.
The children were intubated for longer and needed more oxygen than doctors had anticipated, for example. Doctors in the United States will also need to learn how to treat adults who might become severely ill.
There is no specific treatment for measles, although some are being developed. Doctors primarily rely on antiviral drugs and supportive care.
—
This article originally appeared in The New York Times.
By Apoorva Mandavilli and Dani Blum/Rachel Wisniewski
c. 2026 The New York Times Company